When a patient on warfarin needs urgent surgery, time suddenly has a price tag. OR minutes, ICU beds, staff overtime, everything starts ticking. That’s why hospitals build “reversal readiness” into their playbooks: clear order sets, stocked carts, trained teams, and a safe, fast path to normalize clotting before the incision. In that toolkit, you’ll often find a four-factor prothrombin complex concentrate (4F-PCC), for example, Balfaxar, used under clinician guidance to reverse vitamin K antagonist (VKA) effects in adults who need an urgent procedure.

Via Pexels
First Principles: What “Reversal” Actually Means
Warfarin (a VKA) reduces the body’s ability to make several vitamin-K-dependent clotting factors (II, VII, IX, X). The result is a higher INR, which makes bleeding more likely during surgery. “Reversal” means restoring those factors fast enough and safely enough to allow urgent procedures to proceed. In practice, teams rely on a small set of tools: vitamin K, fresh frozen plasma (FFP), and 4F-PCCs. Guidelines and clinical reviews align with that core toolkit.
The Tools, Translated—Speed vs. Durability vs. Logistics
* Vitamin K: Restores the body’s ability to synthesize clotting factors. It’s important for durable correction but isn’t rapid on its own; clinicians commonly pair it with other agents so INR doesn’t rebound later.
* Fresh Frozen Plasma (FFP): Historically used, still a fallback when PCC isn’t available. But plasma requires thawing and larger volumes, which can slow things down and stress patients with cardiac/renal issues.
* 4F-PCC: Delivers concentrated factors II, VII, IX, and X in a small volume, enabling rapid INR correction—often around the time frame needed to move a patient to the OR. Contemporary guidance generally prefers 4F-PCC (with vitamin K) for urgent warfarin reversal; FFP is reserved for when PCC isn’t available.
Why Modern Pathways Favor 4F-PCCs
For urgent surgery or invasive procedures in warfarin-treated adults, expert pathways advise a 4F-PCC-based strategy because it’s fast, targeted, and predictable at the bedside. Recent overviews and consensus statements reinforce this direction and help standardize practice across pharmacy, anesthesia, and surgery.
What “Fast” Looks Like in Real Life
Hospitals track practical metrics: door-to-dose time, dose-to-INR-correction, and reversal-to-incision. Literature and reference texts describe 4F-PCC achieving rapid INR normalization (about an hour by protocol targets), which is why it anchors many urgent pathways, always under clinician judgment and with vitamin K for sustained effect.
Safety, Governance, and Labels (Read This Part Twice)
4F-PCCs are high-alert biologics. Labels warn about thromboembolic events and the need for careful patient selection and monitoring. That’s why reversal is never a “standing order”, it hinges on clinician risk, benefit decisions, local policy, and post-dose monitoring (e.g., INR checks, watch for thrombosis). Your governance job: make it easy for clinicians to do the right thing quickly, clear indications in the order set, built-in vitamin K prompts, and mandatory documentation of rationale and timing.
Balfaxar in Context: a Rapid-Readiness Example
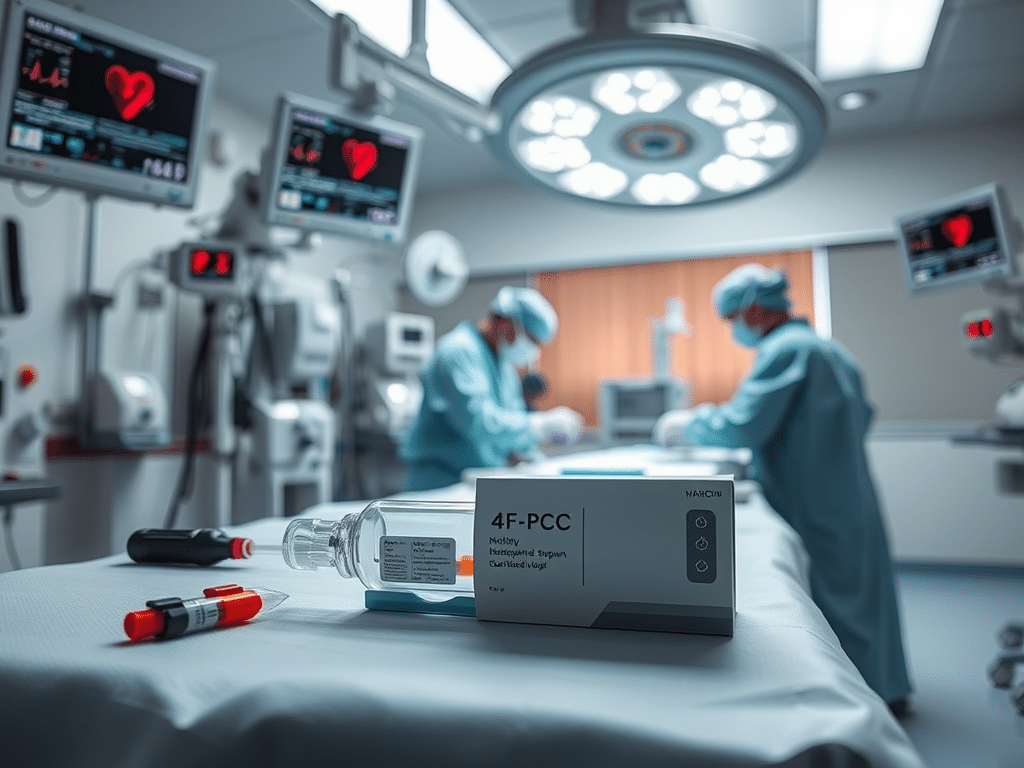
Balfaxar is an FDA-approved 4F-PCC indicated for the urgent reversal of acquired coagulation factor deficiency induced by VKA (e.g., warfarin) therapy in adult patients who need an urgent surgery or invasive procedure. It’s manufactured by Octapharma and sits in the same therapeutic class as other 4F-PCCs used in U.S. practice. In other words, it’s one of the branded options a hospital might standardize on within a clinician-led protocol for perioperative reversal.
In operational terms, the presence of Balfaxar (or an equivalent 4F-PCC) doesn’t replace policy; it enables policy. Pharmacy ensures availability and traceability; nursing verifies patient identity, product, and dose; anesthesia and surgery align on timing relative to incision; and everyone documents outcomes (INR, hemostasis in the field, need for additional blood products). The entire pathway is only as strong as the coordination behind it.

Via Pexels
Where This Shows Up in Your Workflow
- Pre-op huddles & escalation: OR charge nurses and anesthesia confirm anticoagulation status early. If warfarin pops up and the case is urgent, they escalate to the reversal pathway immediately.
- Order sets that guide—not guess: Smart order sets prompt clinicians to select a 4F-PCC, co-administer vitamin K when indicated, and schedule follow-up INR checks at defined time points. They also capture contraindications and reminders about thromboembolic risk.
- Stocking & storage: Pharmacy keeps 4F-PCC in controlled locations (e.g., OR satellite, ED, main pharmacy) with barcode scanning and lot tracking to support pharmacovigilance.
- Time stamps that matter: Track “decision to reverse,” “dose start,” “dose end,” “INR recheck,” and “incision.” These become your QI metrics for throughput and safety.
- After-action reviews: If a case took too long to dose or INR correction lagged, you learn and tune the pathway (supply chain, education, order set design).
The Business Case (Because Operations are Clinical, Too)
A faster, safer path to incision reduces cancellations, shortens anesthesia time, and curbs avoidable bed days from delayed cases. On paper, 4F-PCCs can look pricey per vial; in reality, the total cost of delays, idle OR staff, surgeon time, re-booking, and extra monitoring often dwarfs the unit price. The goal isn’t to “buy drug X.” It’s to buy time and reduce risk. Your finance partners will get it if you track the right metrics and show fewer turnaround bottlenecks after pathway adoption.
Vitamin K Still Matters—Here’s Why
Even when a 4F-PCC rapidly corrects INR, vitamin K provides the durable fix because warfarin’s effect can outlast the infused factors. Many guidelines recommend co-administration for sustained correction, letting the surgical team focus on the case rather than chasing INR later. Your order sets should nudge this step by default (unless a clinician opts out for a specific reason and documents it).
Different Labels, One Clear Pathway
You’ll see small but important differences from brand to brand. In the U.S., Kcentra covers two situations: acute major bleeding and urgent surgery/invasive procedures. Balfaxar’s U.S. label, by contrast, focuses on adults on VKA therapy who need urgent surgery or another invasive procedure. Your hospital protocol should spell this out and steer major-bleeding cases down the right path, based on policy, what’s available, and, above all, clinician judgment.
What to Measure (So You Can Prove This is Working)
- Time to dose: Decision → product at bedside → infusion start.
- INR correction window: Baseline → post-dose target (and timing of that check). Reference points from clinical texts reinforce why this timing matters for safe incision planning.
- OR throughput: Delays avoided, turnarounds improved, cancellations reduced.
- Safety events: Thromboembolic events, re-operation for bleeding, and transfusion needs.
- Protocol adherence: Was vitamin K given where indicated? Was monitoring documented?
Quick FAQ (for Non-Clinicians Who Still Need to Make Decisions)
Is This About All Blood Thinners?
No. This article focuses on warfarin (VKA) reversal before urgent procedures. Direct oral anticoagulants (DOACs) have different pathways and, in some cases, specific antidotes. Policies should clearly separate these flows.
If 4F-PCC is Preferred, Why Keep Plasma?
Because real hospitals deal with supply, storage, and edge cases. Plasma remains a fallback if a 4F-PCC isn’t immediately available, though it’s slower and higher-volume.
Who Makes the Call and How Fast?
Treating clinicians do, ideally within a standardized pathway that compresses decision-to-dose time and bakes in monitoring and documentation. Consensus statements exist to guide that process, and your job is to enable them with operations that work under pressure.
Conclusion: Build Readiness You Can Trust
If you remember one thing, make it this: reversal isn’t a product, it’s a system. When your order sets, stocking plans, training, and metrics line up, clinicians can correct INR quickly, proceed to the OR with confidence, and keep patients safer, all while protecting your throughput. Start with a clear policy, an agreed 4F-PCC strategy plus vitamin K for durability, and measure what matters. Everything else, cost, speed, outcomes, follows. (Educational content only; clinical decisions remain with the treating team.)
Discover more from The Cameron Journal
Subscribe to get the latest posts sent to your email.